


VIP Therapy for CIRS: Risks, Side Effects, and When to Start
What the Shoemaker Protocol, human studies, and mechanistic research reveal about treatment sequencing, adverse effects, dosing, and patient selection.
Editorial Update— July 31, 2026
Our clinical approach tends to err on the side of caution, particularly when supporting individuals with complex chronic illness. This article originally began with Dr. Ritchie Shoemaker’s published protocol, CIRS-specific studies, and clinical guidance from practitioners working within the Surviving Mold framework. We have since expanded the review to include the broader VIP and aviptadil literature, including randomized human trials, clinical safety studies, pharmacology research, human cellular studies, and animal research published across major peer-reviewed medical journals.
This broader review provides a more complete picture.
VIP has been documented to cause acute adverse effects in human studies and to have meaningful biological effects on vascular function, gastrointestinal signaling, immune regulation, mast cells, sleep, circadian rhythms, and the central nervous system. At the same time, controlled research on months or years of chronic intranasal VIP use remains limited, particularly in patients with CIRS, MCAS, ongoing environmental exposure, elevated inflammatory markers, psychiatric vulnerability, or concurrent psychotropic medications.
Some language in the prior version conveyed greater certainty about severe or lasting outcomes than the currently available human literature can establish. We revised those statements while preserving concerns supported by VIP’s known pharmacology, documented human adverse events, mechanistic research, preclinical findings, clinical observations, and the important gaps in long-term safety research.
Limited human evidence should not be interpreted as proof that a treatment is harmless. Mechanistic, cellular, and animal research can identify biologically credible risks, explain why certain patients may respond differently, and guide patient selection and monitoring. These forms of evidence cannot, by themselves, determine how often a specific outcome occurs in people or establish that it will occur in every patient.
These revisions do not diminish the importance of VIP timing, environmental safety, protocol readiness, inflammatory status, patient selection, formulation, dosing, concurrent medications, or clinical monitoring. They distinguish findings documented in human studies from concerns supported primarily by mechanistic or preclinical research, while acknowledging that the absence of definitive trials leaves important questions unresolved.
Judy’s Note: We are committed to providing the most accurate and useful information available at the time of writing. Science, clinical understanding, and available evidence continue to evolve, and when new information meaningfully changes our interpretation, we will update our work openly and with humility. Our purpose is not to defend a fixed position, but to continue learning in service of better root-cause care. Our mission will always be wellness for all.
Articles like this may challenge established clinical practices or complicate decision-making. That discomfort should not prevent careful examination of the evidence. Practitioners have a responsibility not only to recommend interventions, but also to understand them deeply, communicate their benefits and limitations clearly, and help patients make informed decisions. This article is intended to support more thoughtful conversations, stronger clinical judgment, and better-informed care.
What Was Updated
- Updated the title from “The Risks and Nuances of Starting VIP Too Early” to “VIP Therapy for CIRS: Risks, Side Effects, and When to Start” to better reflect the article’s broader, evidence-based focus.
- Clarified that this review draws from both Shoemaker Protocol guidance and the broader VIP and aviptadil literature.
- Clarified the specific readiness criteria used before full-dose VIP and distinguished evidence of reduced efficacy from evidence of treatment-related injury.
- Preserved caution regarding ongoing exposure, VCS, MARCoNS, environmental testing, serum lipase, inflammatory status, dosing, and clinician oversight.
- Revised or removed categorical statements regarding T-cell exhaustion, EBV reactivation, persistent NK-cell suppression, fibrosis, lasting immune impairment, and permanent VIP intolerance where clinical evidence remains limited or indirect.
- Expanded discussion of VIP’s documented human adverse effects, primarily from intravenous studies, and its broader effects on Th1, Th2, Th17, Treg, mast-cell, circadian, sleep, vascular, and neurological pathways based on human, cellular, and animal research.
- Added greater context for individuals with MCAS, migraine susceptibility, significant psychiatric histories, or concurrent serotonergic and other psychotropic medications.
- Clarified that VIP’s short plasma half-life does not mean all downstream cellular or physiological effects necessarily end within minutes.
- Clarified that low-dose compounded titration strategies are based primarily on clinical experience and individualized tolerance rather than comparative trials.
- Added an FAQ explaining known short-term risks, the limits of available percentage estimates, and why adverse-event rates from intravenous trials cannot be directly applied to compounded intranasal VIP.
- Added an evidence table separating human outcomes, mechanistic and preclinical findings, and remaining research gaps.
- Added a dedicated reference section at the end of the article (rather than linking sources only within the text) with brief notes explaining each study’s findings, limitations, and relevance.
In plain terms, the prior version expressed some biologically plausible concerns with more certainty than the current human evidence can support. The revised article does not treat limited human evidence as proof that VIP is safe under all conditions. It retains appropriate caution based on protocol sequencing, documented adverse effects, biological mechanisms, preclinical research, individual susceptibility, and clinical observations, while clearly distinguishing what is known, what is biologically plausible, and what remains uncertain.
What Is VIP Therapy?
Vasoactive intestinal peptide, or VIP, is used as a later-stage therapy in the Shoemaker Protocol for selected patients with Chronic Inflammatory Response Syndrome (CIRS). VIP may support neuroendocrine, immune, vascular, and brain-related recovery, but it is biologically active and can cause side effects. This article explains when VIP is generally considered, what readiness criteria are commonly reviewed, what human studies have documented, and what remains uncertain about starting treatment too early.
CIRS recovery is a delicate, nuanced process that generally follows a precise order. Shoemaker’s published VIP research evaluated selected patients after applicable preceding treatment steps, and his current guidance places VIP at the end of the protocol. The strongest CIRS-specific evidence supports careful sequencing because unresolved exposure, abnormal VCS, and persistent MARCoNS may reduce treatment efficacy, not because severe or permanent harm from “early VIP” has been directly established. [1,2,3]
We’ll explore why timing and patient selection still matter, what human studies have documented about VIP’s benefits and adverse effects, what cellular and animal research suggests mechanistically, and what remains uncertain about chronic intranasal use.
What Is CIRS?
Chronic Inflammatory Response Syndrome, or CIRS, is a multifaceted condition that affects numerous systems throughout the body and can manifest in a wide range of symptoms. At its core, CIRS stems from a dysregulated immune response that leads to persistent, often overwhelming inflammation.
Diagnosing CIRS isn’t straightforward. It demands a holistic and investigative approach, including in-depth lab testing and a careful review of a patient’s health history to uncover patterns, symptoms, and environmental or infectious triggers.
Because of its broad and often confusing symptom picture, CIRS is frequently overlooked or misdiagnosed. It typically doesn’t show up on standard autoimmune panels, making it easy to miss in conventional medical settings. Accurately identifying CIRS requires specialized tools and clinical insight to pinpoint the root causes. This targeted evaluation is essential for developing a treatment strategy that goes beyond symptom management and focuses on true, long-term recovery.
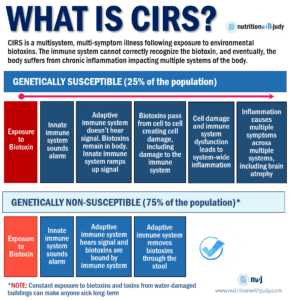
In CIRS, the immune system becomes highly reactive, often due to exposure to biotoxins—harmful substances that can provoke or intensify symptoms in genetically susceptible individuals. These toxins can come from various environmental and biological sources, including:
- Mold and Microbes in Water-Damaged Buildings: A significant portion of CIRS cases, estimated at around 80%, can be traced back to environments affected by water damage. These buildings often harbor mold spores, bacteria, and microbial fragments that linger in the air. Alarmingly, even dead mold particles can trigger severe immune responses and inflammation in sensitive individuals, impacting both cognitive and physical well-being.
- Insect Bites and Vector-Borne Illnesses: Certain bug bites, especially from ticks and spiders, can introduce pathogens like Borrelia burgdorferi (Lyme disease) and Babesia microti. Additionally, bites from recluse spiders have been associated with chronic symptoms in predisposed individuals, sometimes acting as a catalyst for CIRS.
- Toxin-Laden Seafood: Eating certain reef fish contaminated with ciguatoxins, a result of algal blooms, can expose individuals to dangerous biotoxins. These toxins accumulate as smaller fish are eaten by larger ones, making consumption of top predators particularly risky.
- Exposure to Contaminated Water: Lakes and rivers affected by harmful algal blooms, such as cyanobacteria or Pfiesteria, can release toxins that trigger immune activation. Inhalation or skin contact with contaminated water may be enough to contribute to CIRS onset or progression.
- Additional Biotoxin Sources: Other contributors include viral infections, some vaccines, volatile organic compounds (VOCs), endotoxins, and actinomycetes—all of which can challenge the immune system and worsen symptoms in those with CIRS.

Biotoxins are tiny, stealth-like molecules capable of slipping through cell membranes, which makes them incredibly difficult to detect using standard blood work. These toxic compounds often enter the body through breathing in contaminated air, but they can also be absorbed by eating tainted food, experiencing insect bites, or coming into contact with polluted water sources.
Interestingly, not everyone exposed to mold or other biotoxins will go on to develop CIRS. A person’s genetic makeup and life history play a crucial role in whether CIRS takes root. Certain life events—such as major illness, surgery, high fevers, pregnancy, chemical exposure, or emotional trauma—can overwhelm the immune system and spark what’s known as a cytokine storm. For individuals carrying specific HLA-DR genetic variants, this heightened immune reaction can activate CIRS, even if they’ve tolerated similar exposures in the past.
In many people, the body naturally identifies and removes biotoxins. But those with CIRS-prone genetics often lack the immune capacity to recognize and eliminate these invaders, leading to toxin buildup, chronic inflammation, and lingering symptoms. This makes biotoxin illness especially insidious: it can begin suddenly, progress silently, and persist for years without a clear cause.
Even if you’re not currently experiencing symptoms, genetic testing can provide valuable insight into your risk for CIRS and help guide preventative or therapeutic strategies.
For a more detailed understanding of CIRS, click here.
Pro-Tip: If you think you’re suffering from CIRS, you can learn more about CIRS diagnostic testing here.
What Is the Shoemaker Protocol?

The Shoemaker Protocol uses a sequenced approach, with VIP generally considered after applicable preceding steps are addressed.
The Shoemaker Protocol, created by Dr. Ritchie Shoemaker, offers a systematic and clinically validated approach to treating CIRS and other biotoxin-related illnesses. It is currently the only peer-reviewed protocol specifically designed to address the complex, multi-system inflammation seen in these conditions. Rather than focusing solely on symptom management, the protocol provides a step-by-step roadmap that targets the immune dysregulation and biochemical imbalances at the root of CIRS.
The process begins with identifying and removing the sources that may be perpetuating the inflammatory response. While this often includes reducing biotoxin exposure, the broader goal is to lower the total body burden that overwhelms immune function.
Once that burden is reduced, the next phase involves the use of binding agents such as Cholestyramine (CSM) or Welchol to help the body clear out lingering biotoxins. These binders assist in interrupting the cycle of immune activation by physically removing toxins that continue to recirculate and trigger inflammation.
Subsequent steps focus on rebalancing the immune system, stabilizing inflammatory markers, correcting hormone dysregulation, and improving communication between various systems of the body. The goal is to restore resilience and function through carefully sequenced interventions.
The final step of the Shoemaker Protocol is the introduction of VIP (Vasoactive Intestinal Peptide)—a therapeutic tool reserved for when the body is ready. This step is only implemented after key markers have normalized, signaling that the immune system is stable enough to receive deeper regulatory support.
Each stage of the protocol builds upon the last, making timing and precision critical to long-term healing and remission.
What Is VIP?

VIP is a signaling molecule made by nerve cells, immune cells, and the gut. Think of it as a multitasking messenger that helps regulate the immune system. Some of its key roles include:
- Modulates inflammation and cytokine signaling. VIP can reduce selected pro-inflammatory signals, including TNF-alpha and IFN-gamma, while influencing several immune pathways. Its effects are broad and context-dependent, rather than uniformly anti-inflammatory across all settings.
- Supports regulatory immune responses. VIP can increase IL-10 and promote regulatory T-cell activity in experimental systems and in a small inhaled-VIP study in sarcoidosis. These effects may be helpful in inflammatory disease, but they also confirm that VIP meaningfully changes immune function. [4,5]
- Guides how the immune system responds. VIP plays a key role in how T cells, the immune system’s coordinators, function. It helps balance different types of T cells, which can either promote inflammation or regulate it. This balance is critical in conditions like CIRS, autoimmunity, and chronic infections.
- Influences blood vessel tone and circulation. VIP relaxes vascular smooth muscle and can improve selected hemodynamic measures, but the same vasodilatory action can also cause flushing, headache, palpitations, tachycardia, or hypotension depending on dose and route. [6,7,8]
- Supports digestion and gut function. VIP helps regulate how much digestive fluid is produced, how quickly food moves through the gut (motility), and the health of the gut lining. This is crucial for nutrient absorption and preventing leaky gut.
- Participates in sleep, circadian, memory, and mood-related signaling. VIP is central to communication within the suprachiasmatic nucleus, the body’s primary circadian clock. Human administration has altered NREM–REM cycle timing, but whether chronic intranasal VIP improves or disrupts sleep, energy, or mood in a particular patient has not been adequately studied. [9,27]

In Shoemaker’s published CIRS work, VIP is used as the final step after the applicable preceding interventions. In a small open-label study of 20 carefully selected patients, intranasal VIP was associated with improvements in symptoms, inflammatory and hormonal measures, pulmonary pressure during exercise, and quality of life. Later CIRS publications reported transcriptomic and brain-volume changes during VIP treatment. These findings are encouraging, but the studies were not large randomized trials and do not establish that every patient will respond similarly. [2,10,11]
- Improve selected CIRS symptoms and physiological measures
- Support immune and neuroendocrine regulation
- Improve low MSH and other biomarkers in some patients
- Support brain-volume and cognitive changes reported in selected CIRS cohorts
- Help maintain recovery or remission in appropriately selected patients
Why VIP Timing and Patient Selection Should Be Nuanced

Shoemaker’s current criteria for full-dose VIP include a normal VCS test, negative MARCoNS culture, normal HERTSMI-2, normal serum lipase, and no significant ongoing exposure. Older guidance also used ERMI at or below 2 and HERTSMI-2 at or below 10 as environmental targets. Relevant inflammatory and neuroendocrine markers are still being reviewed, but the available guidance does not require that TGF-β1, C4a, and MMP-9 be fully normalized as a universal safety boundary. [1,2]
Starting VIP therapy requires normalized inflammatory markers due to the following:
Protocol Readiness and Reduced Efficacy
Shoemaker’s 2013 VIP study did not compare patients who started VIP early with patients who started it later. The formal trial included 20 refractory CIRS patients who had already completed the applicable sequential treatment steps and then used intranasal VIP for at least 18 months. [2]
- Clinical experience described in that paper identified three factors associated with reduced efficacy: an abnormal VCS, ERMI above 2, and persistent MARCoNS. Patients with those findings were excluded from the formal trial. This supports completing the earlier protocol steps and avoiding significant ongoing exposure, but it does not show that VIP routinely causes severe or permanent injury when those criteria are not met. [2]
- A 2026 retrospective study of 188 adults treated within a CIRS-informed framework provides additional human evidence that MARCoNS status may matter within the broader treatment sequence. Patients who were MARCoNS-negative at follow-up had higher circulating α-MSH than patients who remained positive. The study did not find a corresponding MARCoNS-related difference in VIP or MMP-9 trajectories and was not designed to test whether positive MARCoNS makes VIP harmful. It strengthens the rationale for addressing persistent sinonasal colonization, but does not prove a VIP safety threshold. [3]
VIP is a Powerful Immunomodulator
VIP influences T-cell function, antigen presentation, cytokine signaling, regulatory pathways, and innate immune activity. These effects help explain why VIP may be therapeutic, but they also support individualized timing and monitoring rather than treating VIP as biologically inert.

T cells are a type of white blood cell that play a central role in how your immune system responds to threats. There are different kinds of T cells, and each has a specific job. Here’s what they do:
- Helper T cells (Th cells): These are like the “managers” of the immune system. They don’t fight directly, but they give instructions to other immune cells using signaling chemicals called cytokines. Their job is to coordinate a proper immune response when your body senses infection or danger.
- Regulatory T cells (Tregs): These are the peacekeepers of your immune system. They make sure your immune system doesn’t go overboard and start attacking your own healthy tissues—something that happens in autoimmune diseases.
- Cytotoxic T cells (also called CD8+ T cells): These are the soldiers of your immune system. They find and destroy cells that are infected with viruses or have turned cancerous.
- Th1 cells (a subset of helper T cells): Th1 cells are inflammation-promoting cells that help fight viruses and certain bacteria. They activate parts of the immune system that use inflammation as a weapon, which is useful short term, but can become a problem if stuck in overdrive.
- Th2 cells (another subset of helper T cells): These are more active during responses to parasites and allergens. They help your body produce antibodies and can also contribute to allergies and histamine problems if they become too dominant.
- Th17 cells (yet another subset of helper T cells): Th17 cells help fight fungi and bacteria that live outside cells (like on your skin or in the gut). However, they’re also heavily involved in autoimmune conditions and chronic inflammation when overactive.
A 2010 study using activated human T cells in vitro (outside the body) found that VIP could slow cell growth and division, pause the normal cell cycle, and increase levels of FoxP3 and CTLA-4. These are markers associated with regulatory T cells, which help calm or restrain immune activity. The effects remained measurable after the initial VIP exposure ended in the laboratory. However, the study did not show that VIP causes harmful T-cell exhaustion or long-term immune suppression in patients. [4]
T-cell exhaustion is a specific dysfunctional state most clearly characterized in chronic antigen exposure, cancer, and persistent infection. No human study has shown that intranasal VIP causes T-cell exhaustion, EBV reactivation, or impaired control of infection. Animal and laboratory studies show that VIP can reduce the activity of certain virus-fighting immune cells, including natural killer (NK) cells and activated T cells, under some conditions. This makes antiviral immune function a reasonable area to monitor, but human studies have not shown that VIP causes clinically significant antiviral suppression. [18]
VIP often quiets certain Th1 immune pathways, which help fight infections but can also contribute to autoimmune inflammation when they remain overactive. VIP can also promote regulatory T cells, which help prevent the immune system from attacking healthy tissue, and may shift activity toward Th2 pathways, which are more involved in antibody, allergy, and histamine responses. Studies using human immune cells have documented VIP-related increases in regulatory T-cell activity, FoxP3, CTLA-4, IL-10, and Th2-associated responses. [4,12,13]
In one laboratory study using mouse T cells, VIP combined with TGF-β increased the production of a distinct type of Th17 cell that produces IL-17. Th17 cells help defend against certain bacteria and fungi, but excessive Th17 activity contributes to autoimmune diseases such as rheumatoid arthritis, lupus, multiple sclerosis, psoriasis, and inflammatory bowel disease. [14]
Other animal studies found the opposite effect: VIP reduced Th17 and Th1 activity, increased regulatory T-cell activity, and improved disease findings in experimental rheumatoid arthritis, lupus nephritis, and autoimmune diabetes. [15,16,17]
These findings suggest that VIP’s immune effects depend on the surrounding immune environment, receptor activity, disease model, dose, and timing. They do not demonstrate that elevated blood TGF-β1 levels will lead to harmful Th17 dominance in patients receiving intranasal VIP.
VIP may also affect mast cells. In cultured human mast cells, VIP has been shown to trigger degranulation and the release of cytokines and chemokines. IgE activation also increased VPAC2 receptor expression and mast-cell responsiveness to VIP. These findings provide a plausible reason to use greater caution in individuals with MCAS or significant histamine sensitivity. Clinically, we often find that these patients require a slower, more careful introduction of VIP, even when they meet Shoemaker protocol criteria for treatment. However, clinical studies have not yet established how often intranasal VIP worsens MCAS symptoms. [19]
VIP therefore should not be described as either a universally calming peptide or a predictable cause of immune dysfunction. Its effects can vary by dose, route, receptor expression, tissue, immune context, and individual susceptibility.
What Remains Uncertain About Immune Risk
In some animal studies, blocking VIP signaling strengthened antiviral or antitumor immune responses. This suggests that the body’s natural VIP signaling can suppress cellular immunity in certain situations. However, these findings do not demonstrate that intranasally administered VIP weakens antiviral immunity in people with CIRS. [18]
TGF-β1 is a relevant inflammatory marker in CIRS, and VIP can interact with TGF-β-dependent immune pathways.
Current research has not established:
- A TGF-β1, C4a, or MMP-9 threshold that reliably separates safe from unsafe VIP use
- That starting VIP before every inflammatory marker is normal causes irreversible intolerance or long-term deterioration
- That intranasal VIP causes EBV reactivation, persistent NK-cell suppression, fibrosis, or permanent immune impairment
What Does the Evidence Actually Show About VIP?
Not every type of research answers the same question. Human clinical studies show what has been observed in treated people under specific conditions. Human cellular, animal, and other mechanistic studies help explain what VIP can do biologically and why certain patients may respond differently. Clinical observations may identify important safety signals before formal trials exist. The table below separates these categories so readers can understand both the evidence supporting caution and the questions that remain unresolved.
| Topic | Human Outcomes | Mechanistic or Preclinical Findings | What Remains Uncertain |
| Protocol timing and exposure | Shoemaker studied VIP after preceding treatment steps. Abnormal VCS, ERMI above 2, and persistent MARCoNS were associated with reduced efficacy; current criteria include normal VCS, HERTSMI-2, lipase, negative MARCoNS, and no significant exposure. [1,2] | Continued exposure can sustain inflammatory signaling and may interfere with treatment response. | No controlled human study has shown that VIP during exposure causes permanent immune injury. |
| MARCoNS | A 2026 retrospective cohort found higher follow-up α-MSH in patients who became MARCoNS-negative; no MARCoNS interaction was seen for VIP or MMP-9. [3] | Persistent sinonasal colonization may interact with mucosal immunity and neuroendocrine signaling. | The study did not test whether positive MARCoNS makes VIP harmful or prove that clearance caused the α-MSH change. |
| Acute vascular and gastrointestinal effects | IV trials document hypotension, diarrhea, flushing, tachycardia, palpitations, and infusion reactions. [6,8,23] | VPAC receptor and cAMP signaling cause vasodilation, smooth-muscle relaxation, and intestinal secretion. | Rates from critically ill IV-treated patients cannot be applied directly to lower-dose intranasal VIP. |
| Migraine, headache, and tiredness | A randomized trial provoked migraine in 71% of migraine patients after a two-hour IV VIP infusion; tiredness and other acute symptoms were reported. [7,20] | VIP activates cranial vasodilatory and trigeminovascular pathways. | The frequency and severity of these reactions with intermittent intranasal treatment are unknown. |
| T cells and immune regulation | Inhaled VIP increased regulatory T-cell activity in a small sarcoidosis study. [5] | Human T-cell studies show cell-cycle arrest, FoxP3/CTLA-4 expression, and suppressive regulatory activity. [4] | These findings do not establish pathological T-cell exhaustion, chronic immunodeficiency, or EBV reactivation in CIRS. |
| TGF-β and Th17 | No human trial has shown that elevated serum TGF-β1 converts VIP into a harmful therapy. | VIP plus TGF-β promoted a distinctive Th17 population in one preclinical model; other models show reduced Th17 activity. [14,15,17] | No validated TGF-β1 threshold predicts VIP tolerance, immune injury, or treatment benefit. |
| MCAS and mast cells | Controlled trials have not quantified MCAS reactions to intranasal VIP. | VIP induced degranulation and mediator release in cultured human mast cells; IgE activation increased VPAC2 responsiveness. [19] | The frequency, dose relationship, and clinical significance in MCAS remain unknown. |
| Sleep, circadian rhythm, and fatigue | IV VIP altered NREM–REM cycle timing in healthy men; tiredness was reported in the migraine trial. [7,9] | VIP is central to circadian synchronization and REM regulation in animal and ex-vivo research. [27] | Chronic intranasal studies have not systematically assessed insomnia, fragmented sleep, or persistent fatigue. |
| SSRIs and psychiatric symptoms | No human study has established a clinically significant VIP–SSRI interaction. Major trials did not systematically monitor mood, suicidality, or psychotropic interactions. | Older rat studies show VIP can influence serotonin release and uptake in the suprachiasmatic area. [21,22] | It is unknown whether usual intranasal dosing alters human serotonin transport or contributes to mood destabilization. |
| Long-term intranasal safety | Shoemaker’s 20-person open-label study reported no significant safety signal during at least 18 months in selected patients. [2] | VIP is rapidly cleared from plasma, but receptor signaling can produce downstream cellular effects that outlast circulating peptide. [4,9,27] |
There are no large randomized long-term trials of chronic intranasal VIP, including in MCAS, psychiatric, infectious, or highly inflamed populations. |
This evidence does not support describing VIP as either harmless or inherently dangerous. VIP has been documented to cause acute adverse effects in humans and to exert broad biological effects on vascular function, gastrointestinal secretion, immune regulation, mast cells, sleep, circadian rhythms, and neurological signaling. Mechanistic and preclinical findings identify credible reasons for caution in certain patients, but many specific long-term outcomes have not been directly studied.
What Human Trials Have Documented
Most human safety studies have tested VIP as a short-term intravenous (IV) infusion, not as long-term intranasal treatment. In the 461-patient TESICO trial, participants received aviptadil through three 12-hour infusions over three days. Flushing, hypotension, diarrhea, rapid heart rate, treatment pauses, and treatment discontinuation occurred more often with aviptadil. Serious safety events were also somewhat more common, although the difference was not statistically significant. These results cannot be directly applied to intranasal VIP use in CIRS, but they show that VIP can produce meaningful short-term effects in the body. [6,8,23]
A randomized crossover study in 21 people with migraine found that a two-hour VIP infusion provoked migraine in 15 participants compared with one after placebo. Other reported effects included flushing, warmth, heart palpitations, cold sensations, abdominal discomfort, back pain, tiredness, and diarrhea. Migraine susceptibility is therefore a reasonable monitoring consideration, even though the relevance to intermittent intranasal dosing remains uncertain. [7,20]
VIP has a very short plasma half-life because the intact peptide is rapidly broken down by enzymes. Early human intravenous studies reported a disappearance half-life of approximately 1 minute, while later pharmacokinetic studies described two elimination phases of approximately 2 and 21 minutes. Therefore, the commonly cited one- to four-minute half-life reasonably describes VIP’s initial rapid clearance, although a smaller amount may remain during a slower terminal phase. [28, 29]
This rapid clearance limits the time intact VIP remains in circulation, and many of its immediate vascular, gastrointestinal, and secretory effects are measured over minutes to hours rather than days or months. However, that does not mean every downstream effect ends when the peptide is cleared. Receptor activation can influence gene transcription, immune-cell behavior, vascular responses, and neural timing beyond the immediate exposure period. This biological persistence does not prove permanent injury, but it does mean that the short plasma half-life alone cannot be used to dismiss a sustained reaction. [4,9,27]
Long-term controlled safety data for chronic intranasal VIP remain sparse. Shoemaker’s open-label CIRS study provides preliminary reassurance for carefully selected patients treated after the preceding steps, but it cannot reliably identify uncommon adverse effects, compare early with protocol-timed VIP, or establish universal safety across MCAS, psychiatric, infectious, or highly inflamed populations. [2]
Aviptadil has received investigational and orphan-drug designations for selected indications, but it is not FDA-approved in the United States for CIRS. Compounded intranasal VIP is also not an FDA-approved CIRS treatment. [24]
Where VIP Stands Now: Our Current Position
VIP remains a potentially valuable later-stage therapy for appropriately selected patients with CIRS. Shoemaker’s small open-label CIRS studies and related publications report improvements in symptoms, selected biomarkers, exercise-related pulmonary pressure, quality of life, gene expression, and brain volume after patients completed the applicable preceding protocol steps. Broader human research also confirms that VIP can exert meaningful vascular and immunoregulatory effects. These findings justify continued clinical interest in VIP, while the limited study designs mean that benefit cannot be assumed for every patient. [2,5,6,8,10,11]
Known human risks include:
- headache or migraine,
- tiredness,
- flushing,
- palpitations,
- tachycardia (rapid heart rate),
- hypotension (low blood pressure),
- diarrhea, and
- other route- and dose-dependent reactions.
Human cellular and preclinical research also supports careful attention to immune context, mast-cell reactivity, sleep and circadian changes, neurological symptoms, and individual medication sensitivity. These mechanisms are relevant to informed consent and monitoring, even though they do not establish how often severe or persistent reactions occur during chronic intranasal treatment. [4,6,7,8,9,18,19,20,21,22,23,27]
Current evidence does not show that administering VIP before every inflammatory marker has normalized routinely causes permanent immune injury, T-cell exhaustion, or irreversible intolerance. It also does not prove that VIP is equally safe or effective when significant exposure, positive MARCoNS, failed VCS, abnormal lipase, or other unresolved protocol issues remain. The strongest CIRS-specific rationale is therefore to use VIP as a sequenced therapy rather than an automatic next prescription: complete the applicable earlier steps, confirm readiness, discuss known and uncertain risks, and individualize dosing and monitoring.

Considering Additional Pre-Treatment Screening
Not every patient requires an extensive testing panel before VIP. In addition to confirming the core Shoemaker readiness criteria, prescribers may consider a focused baseline when the history suggests greater vulnerability. This can include a complete medication review; migraine, sleep, mood, suicidality, mast-cell, orthostatic, and cardiovascular history; baseline blood pressure and heart rate; and a record of current symptoms. A PHQ-9 can provide a repeatable mood baseline for patients with current or prior depression, significant mood instability, suicidal ideation, or psychotropic medication use. For patients with suspected MCAS, a structured assessment of symptoms and mediators may include baseline tryptase and event-related tryptase or urinary mediators, when clinically appropriate. Relevant CIRS markers, a CBC with differential, and other inflammatory or neuroendocrine testing may provide context, but no validated VIP-specific immune panel or biomarker cutoff predicts who will react. [25,26]
In our practice, consultation with very experienced CIRS clinicians and mentors has also been valuable for recognizing patterns of sensitivity and identifying patients who may warrant slower titration or closer monitoring, although these clinical observations have not been validated in controlled studies.
Monitoring should be proportional to the patient’s baseline risks rather than applied as an inflexible protocol. Patients with migraine susceptibility, MCAS, marked medication sensitivity, blood-pressure instability, significant psychiatric history, or concurrent serotonergic or other psychotropic medications may warrant slower titration and earlier follow-up focused on mood, sleep, headache, mast-cell symptoms, blood pressure, and heart rate. Repeat PHQ-9 scoring or targeted laboratory testing can be used when the baseline history or new symptoms justify it. New suicidal ideation, a severe mood change, anaphylaxis, symptomatic hypotension, or a disabling migraine requires prompt clinical assessment and generally holding VIP until the reaction has been evaluated. No validated VIP-specific screening or monitoring protocol currently exists; these are informed-consent and risk-management considerations, not universal prerequisites. [7,25,26]
What About Low-Dose VIP at the Beginning or Middle of the Protocol?
Some practitioners use compounded low-dose or diluted VIP earlier in treatment for selected, highly sensitive patients. Dilutions such as 1:100, 1:1,000, or 1:10,000 are clinical titration strategies intended to assess tolerance and reduce abrupt exposure. Comparative trials have not established that one dilution is universally safest, that early microdosing prevents immune complications, or that a specific six-month escalation schedule is required.
These approaches may be reasonable when individualized by the prescribing clinician, but they should not be presented as validated substitutes for exposure control, core readiness criteria, or careful reassessment when symptoms worsen.
Why Am I Not Tolerating VIP Therapy?

There are various factors to troubleshoot if you’re unable to tolerate VIP therapy at this time. Some are supported by Shoemaker’s protocol criteria, while others are informed by mechanistic research or clinical observation rather than controlled trials:
- Ongoing Inflammation or Other Active Illness: Vector-borne illness, chronic infection, uncontrolled inflammatory disease, sleep disruption, or other active stressors may affect tolerance or make it harder to interpret a reaction. These factors should be evaluated individually; they have not been proven to make VIP inherently damaging in every patient.
- MCAS/Histamine Intolerance: Human cellular research shows that VIP can activate certain mast-cell populations. Patients with known or suspected MCAS may warrant slower titration and closer monitoring for flushing, itching, congestion, headache, gastrointestinal symptoms, tachycardia, or other mast-cell-like reactions. MCAS is a monitoring consideration, not an established absolute contraindication. [19]
- Too High of a Dose or Rapid Escalation: Dose, concentration, frequency, formulation, and rate of titration may affect tolerance. Some clinicians start with highly diluted compounded preparations, but there is no universally validated starting dilution or escalation schedule. Highly sensitive individuals may begin at dilutions as low as 1:10,000, while others may tolerate a stronger starting dilution such as 1:100. The starting dose and rate of increase should be individualized by the prescribing clinician based on symptoms and response.
- Persistent MARCoNS or Other Unmet Protocol Criteria: Current Shoemaker guidance calls for a negative MARCoNS culture before full-dose VIP. Earlier Shoemaker research identified persistent MARCoNS, abnormal VCS, and unresolved environmental exposure as factors associated with reduced treatment efficacy. If VIP is not well tolerated or is not producing the expected benefit, MARCoNS status and the other readiness criteria should be reassessed. [1,2,3]
- Being in Exposure: Shoemaker’s guidance states that VIP is not appropriate during significant ongoing exposure and is less likely to work when environmental criteria are not met. New or continued exposure should be reassessed before assuming that symptoms represent a permanent VIP reaction. [1,2]
A small subset of patients may not tolerate VIP despite appropriate sequencing, dose adjustment, and reassessment of contributing factors. In clinical practice, some complete treatment using other individualized options, including LDN or Synapsin Spray, although these alternatives have not been directly compared with VIP in controlled CIRS trials.
Why VIP Timing Matters
To summarize, VIP is generally best considered after the applicable earlier steps have been completed and the patient meets the core readiness criteria. This approach follows the population and sequence in which intranasal VIP has been studied, reduces the chance of ineffective treatment during ongoing exposure, and allows adverse reactions to be interpreted more clearly. It does not require assuming that every inflammatory marker must be fully normal or that earlier use inevitably causes permanent injury.
TLDR: Summary On the Importance of VIP Timing
Here’s a quick overview of everything we’ve discussed:
What Is VIP?
VIP (vasoactive intestinal peptide) is a natural signaling molecule made by nerves, the gut, and immune cells. It affects inflammation, circulation, digestion, immune regulation, sleep, circadian timing, and neurological signaling. In the Shoemaker Protocol, prescribed intranasal VIP is generally used as a final-stage therapy after the earlier steps have been addressed.
Why VIP Should Not Usually Be the First Step
VIP can be beneficial, but it should usually not be used as a shortcut for exposure reduction, binders, MARCoNS treatment, VCS recovery, serum lipase assessment, or other applicable steps of the protocol. Here’s why timing matters:
- Protocol readiness affects the likelihood of benefit. Ongoing exposure, abnormal VCS, and persistent MARCoNS have been associated with reduced VIP efficacy. Current guidance also requires normal HERTSMI-2 and serum lipase before full-dose therapy. [1,2]
- VIP meaningfully changes immune signaling. Human cellular and clinical studies show effects on regulatory T cells, cytokines, and other immune pathways. These findings support monitoring, but they do not prove that early VIP routinely causes T-cell exhaustion or permanent immune suppression. [4,5]
- Certain patients may be more reactive. Human mechanistic data support additional caution in MCAS, while human infusion studies identify migraine susceptibility as a clear risk context. Individual reactions can still differ substantially with intranasal dosing. [7,19,20]
- Known acute effects and long-term gaps both matter. Human studies have documented flushing, headache or migraine, tiredness, palpitations, tachycardia, hypotension, diarrhea, and infusion reactions. Robust long-term controlled data for chronic intranasal VIP are lacking. [6,7,8,20,23]
- Psychiatric history and psychotropic medications deserve attention. No clinically defined VIP–SSRI interaction has been established, but experimental serotonergic and circadian findings, limited psychiatric safety monitoring, and clinical reports of severe mood reactions support coordination among prescribers and prompt reassessment if mood, sleep, agitation, or suicidal thinking changes.
When to Start VIP

The updated protocol criteria are summarized below.
VIP is generally considered after:
- Significant ongoing exposure has been addressed and the environment meets the applicable protocol target
- MARCoNS culture is negative
- The VCS test is normal
- Serum lipase is normal
- HERTSMI-2 is normal (≤10) and the applicable preceding laboratory abnormalities and treatment steps have been reviewed
- Individual risk factors, including MCAS, migraine susceptibility, blood-pressure vulnerability, medication sensitivity, psychiatric history, and concurrent psychotropic medications have been reviewed
Meeting these criteria is consistent with the Shoemaker Protocol and may improve the likelihood that VIP is effective and interpretable. It does not guarantee a reaction-free course, which is why individualized dosing and monitoring remain important.
Timing Is Everything
VIP is powerful, but it can also be an important and beneficial therapy when used in the right clinical context. Following the established sequence helps reduce avoidable uncertainty and gives the treatment the best opportunity to work.
Some people experience acute or unusual reactions. These should be taken seriously and assessed rather than dismissed solely because VIP has a short plasma half-life. The prescriber may need to pause or reduce the dose and reassess exposure, formulation, migraine susceptibility, MCAS, concurrent medications, sleep, and other competing causes.
Current evidence does not show that trying VIP too early will permanently prevent a patient from tolerating or benefiting from VIP later, after contributing factors have been addressed.
Frequently Asked Questions About VIP
1) What are the known risks of VIP, and how common are they?
Known short-term reactions to VIP include:
- Headache or migraine
- Flushing or warmth
- Palpitations
- Rapid heart rate
- Lower blood pressure or lightheadedness
- Diarrhea or abdominal discomfort
- Tiredness
- Other reactions influenced by the dose, formulation, route, and rate of titration
The exact percentage risk for patients using compounded intranasal VIP for CIRS is unknown because no large, controlled trial has evaluated the long-term safety of this specific treatment.
Most available percentages come from IV studies, which expose the body to VIP differently than a nasal spray. In a randomized study of 21 people who already had migraine, a two-hour intravenous VIP infusion triggered migraine in 71%, compared with approximately 5% after placebo. Flushing or warmth occurred in approximately 95%, and palpitations occurred in approximately 81%. These percentages should not be applied to the average person using intranasal VIP because the participants were selected for migraine susceptibility and received a continuous intravenous infusion. [7]
A separate study in healthy volunteers also found that a two-hour intravenous VIP infusion could cause delayed headache and widening of blood vessels outside the skull, supporting migraine or headache susceptibility as a reasonable consideration before treatment. [20]
In the larger TESICO trial involving critically ill hospitalized patients, intravenous aviptadil caused more diarrhea, flushing, rapid heart rate, and low blood pressure than placebo. Diarrhea occurred in approximately 40% versus 11%, flushing in 15% versus 6%, rapid heart rate in 10% versus 5%, and low blood pressure in 58% versus 41%. These rates cannot be directly applied to intranasal VIP because the patients were critically ill and received escalating 12-hour intravenous infusions. [6]
Another randomized trial of intravenous aviptadil in critically ill patients also provides short-term safety data, but it does not establish the percentage risk associated with compounded intranasal VIP used for CIRS. [23]
Smaller inhaled or intranasal studies have generally reported better tolerance. For example, a four-week inhaled-VIP study involving 20 patients with sarcoidosis described treatment as safe and well tolerated. However, studies of this size are not large enough to detect uncommon reactions or establish precise risk percentages for patients with CIRS, MCAS, migraine, psychiatric vulnerability, or substantial medication sensitivity. [5]
2) Are the risks higher when the Shoemaker sequence is not followed?
Shoemaker’s research supports completing the applicable protocol steps before full-dose VIP. Persistent MARCoNS, an abnormal VCS, and unresolved environmental exposure were associated with reduced treatment efficacy. Current guidance also includes normal serum lipase and acceptable environmental testing among the readiness criteria. [1,2]
A 2026 retrospective study provides additional support for addressing persistent MARCoNS within the broader treatment sequence, although it did not show that MARCoNS directly causes VIP reactions. [3]
Current evidence does not establish that starting VIP before the readiness criteria are met causes a higher percentage of adverse reactions or permanent immune damage. The evidence more clearly shows that failing to follow the sequence may reduce the likelihood of benefit and make it harder to determine whether symptoms are coming from VIP, continued exposure, persistent MARCoNS, another active illness, or the dose itself. [1,2,3]
3) What should patients understand before starting VIP?
For an individual patient, risk may be influenced by:
- Dose, concentration, formulation, and speed of titration
- Migraine or chronic-headache history [7,20]
- MCAS or significant histamine sensitivity [19,26]
- Low blood pressure, orthostatic symptoms, palpitations, or cardiovascular sensitivity [6,8]
- Significant medication sensitivity
- Sleep or circadian disruption [9,27]
- Psychiatric history or concurrent psychotropic medications
- Ongoing environmental exposure or other unmet protocol criteria [1,2,3]
Patients with these vulnerabilities may warrant a lower starting dose, slower titration, and closer follow-up. However, there is no validated VIP-specific test or risk calculator that can predict exactly who will react or provide a reliable percentage for an individual patient.
New suicidal thoughts, severe mood changes, fainting, symptomatic low blood pressure, anaphylaxis-like symptoms, a sustained rapid heart rate, or a disabling migraine warrant prompt medical assessment and generally holding further VIP until the prescribing clinician evaluates the reaction.
4) If VIP can normalize TGF-β1, why can’t we use it earlier to fix high TGF-β1 levels?
Because VIP is not a single-marker treatment, and the evidence does not define one TGF-β1 value that determines whether treatment is safe or unsafe.
In Shoemaker’s small, selected CIRS cohort, VIP lowered elevated TGF-β1 after patients had completed the applicable preceding steps. Current public criteria do not require every inflammatory marker to be completely normal. However, VIP and TGF-β interact in context-dependent immune pathways, and no human trial has specifically tested chronic intranasal VIP in patients selected for very high TGF-β1. [1,2,14]
The stronger reason not to use VIP as a shortcut is practical: ongoing exposure, positive MARCoNS, failed VCS, abnormal lipase, or incomplete preceding steps may reduce efficacy and make the patient’s response harder to interpret.
The same principle applies to C4a and MMP-9. VIP improved these markers in Shoemaker’s selected cohort, but no study has demonstrated that it merely suppresses them temporarily and then causes rebound. These markers should be interpreted within the full clinical picture rather than used as isolated reasons to start or withhold VIP. [2]
VIP is intended to support regulation after the foundation: exposure control, binders, MARCoNS treatment, and correction of applicable downstream abnormalities have been addressed.
5) If VIP helps raise androgens (like testosterone), why not use it to fix hormone imbalances sooner?
Since hormone imbalances in CIRS are usually secondary and not the root cause.
Androgens like testosterone or DHEA often fall in CIRS because of:
- Chronic inflammation
- Low MSH (melanocyte-stimulating hormone)
- HPA axis suppression
- Toxic or mold exposure
Shoemaker’s CIRS study reported improvement in androgen measures during the complete treatment sequence, but no controlled trial has validated VIP as an early, stand-alone hormone therapy. Addressing exposure, inflammation, neuroendocrine disruption, nutrition, sleep, and other upstream factors remains essential. [2]
VIP’s effects on immune and endocrine pathways are context-dependent. Hormone changes should therefore be monitored alongside symptoms, exposure status, and the broader laboratory pattern rather than assumed to prove either readiness or harm.
6) Does VIP’s short half-life mean it cannot cause effects that last longer?
No. VIP is rapidly broken down in the bloodstream, which limits how long the intact peptide circulates through the body. However, once VIP activates its receptors, it can start changes in cell signaling, gene activity, immune-cell behavior, blood-vessel function, and circadian rhythms that may continue after the peptide itself has been cleared. This simply means that VIP’s short half-life cannot be used to assume that every biological effect ends within minutes. [4,9,27]
7) Is VIP contraindicated in MCAS or for people taking SSRIs?
Neither MCAS nor SSRI use has been established as an absolute contraindication. Human mast-cell research provides a direct mechanistic reason for additional caution in MCAS. The SSRI concern is less established: experimental research shows VIP can influence serotonergic and circadian pathways, but no human interaction study has demonstrated that intranasal VIP and SSRIs cause serotonin toxicity or predictable mood destabilization. Both situations support individualized risk assessment, coordination among prescribers, and close monitoring. [19,21,22]
Pro-Tip: Are you looking for more in-depth practitioner resources and a like-minded community to support you through your CIRS journey? Join our exclusive CIRS Support Group for the latest research, step-by-step protocol tools, and support to successfully achieve root-cause healing.
Selected References with Notes
- Surviving Mold. 12-Step Protocol Overview. Accessed July 27, 2026. https://www.survivingmold.com/legal-resources/12-step-protocol-overview
This overview presents the Shoemaker Protocol as a sequence of treatment steps, with VIP generally reserved for the final stage after applicable exposure, environmental, infectious, inflammatory, and hormonal issues have been addressed. It is clinical protocol guidance, not a controlled VIP safety trial.
- Shoemaker RC, House DE, Ryan JC. Vasoactive intestinal polypeptide (VIP) corrects chronic inflammatory response syndrome (CIRS) acquired following exposure to water-damaged buildings. Health. 2013;5(3):396–401. doi:10.4236/health.2013.53053 https://www.scirp.net/journal/paperinformation?paperid=28586
This small, open-label study followed 20 carefully selected CIRS patients who used intranasal VIP for at least 18 months after completing the preceding protocol steps. The authors reported improvements in symptoms, quality of life, exercise-related pulmonary pressure, hormones, and selected inflammatory markers, but there was no placebo group or early-versus-late VIP comparison.
- DiTulio M, Navarro-Torres CA. Clearance of multiple antibiotic-resistant coagulase-negative staphylococci is selectively associated with higher circulating α-melanocyte stimulating hormone in patients evaluated for chronic inflammatory response syndrome. Front Endocrinol. 2026;17:1728408. doi:10.3389/fendo.2026.1728408. https://www.frontiersin.org/journals/endocrinology/articles/10.3389/fendo.2026.1728408/full
This retrospective study included 188 adults evaluated within a CIRS-informed framework. Patients who were MARCoNS-negative at follow-up had higher α-MSH than those who remained positive, but MARCoNS status was not associated with corresponding differences in VIP or MMP-9 and the study did not test whether MARCoNS causes reactions to VIP.
- Anderson P, Gonzalez-Rey E. Vasoactive intestinal peptide induces cell cycle arrest and regulatory functions in human T cells at multiple levels. Mol Cell Biol. 2010;30(10):2537–2551. doi:10.1128/MCB.01282-09. PMID:20231362. https://www.tandfonline.com/doi/full/10.1128/MCB.01282-09
This laboratory study used activated human T cells outside the body. VIP slowed their growth and division and promoted markers and functions associated with regulatory T cells, but the study did not show that VIP causes harmful T-cell exhaustion or chronic immune deficiency in patients.
- Prasse A, Zissel G, Lützen N, et al. Inhaled vasoactive intestinal peptide exerts immunoregulatory effects in sarcoidosis. Am J Respir Crit Care Med. 2010;182(4):540–548. doi:10.1164/rccm.200909-1451OC. PMID:20442436. https://pubmed.ncbi.nlm.nih.gov/20442436/
In this open-label phase II study, 20 patients with active sarcoidosis inhaled VIP for four weeks. Treatment was reported as safe and well tolerated and reduced inflammatory TNF-α production while increasing regulatory immune activity, but the study was small and did not involve CIRS or long-term intranasal use.
- Brown SM, Barkauskas CE, Grund B, et al. Intravenous aviptadil and remdesivir for treatment of COVID-19-associated hypoxaemic respiratory failure in the USA (TESICO): a randomized, placebo-controlled trial. Lancet Respir Med. 2023;11(9):791–803. doi:10.1016/S2213-2600(23)00147-9. PMID:37348524. https://pubmed.ncbi.nlm.nih.gov/37348524/
TESICO was a large randomized trial of intravenous aviptadil in hospitalized patients with severe COVID-19 respiratory failure. It did not improve the primary clinical outcome and caused more flushing, diarrhea, rapid heart rate, low blood pressure, infusion interruptions, and treatment discontinuations than placebo; these rates cannot be applied directly to intranasal VIP.
- Pellesi L, Al-Karagholi MA, De Icco R, et al. Effect of vasoactive intestinal polypeptide on development of migraine headaches: a randomized clinical trial. JAMA Netw Open. 2021;4(8):e2118543. doi:10.1001/jamanetworkopen.2021.18543. https://jamanetwork.com/journals/jamanetworkopen/fullarticle/2782759
In this randomized crossover trial, a two-hour intravenous VIP infusion triggered migraine in 15 of 21 people with a history of migraine, compared with one after placebo. Flushing, warmth, palpitations, tiredness, abdominal symptoms, and diarrhea were also reported, although the route and patient population differ from CIRS treatment.
- Frase LL, Gaffney FA, Lane LD, et al. Cardiovascular effects of vasoactive intestinal peptide in healthy subjects. Am J Cardiol. 1987;60(16):1356–1361. doi:10.1016/0002-9149(87)90619-9. PMID:3687785. https://pubmed.ncbi.nlm.nih.gov/3687785/
This study administered intravenous VIP to six healthy adults and measured heart rate, blood pressure, cardiac output, and blood flow. It confirms that VIP has meaningful cardiovascular and vasodilatory effects, supporting attention to palpitations, heart-rate changes, and low blood pressure in susceptible patients.
- Murck H, Guldner J, Colla-Müller M, et al. VIP decelerates non-REM–REM cycles and modulates hormone secretion during sleep in men. Am J Physiol. 1996;271(4 Pt 2):R905–R911. doi:10.1152/ajpregu.1996.271.4.R905. PMID:8897980. https://journals.physiology.org/doi/abs/10.1152/ajpregu.1996.271.4.R905
This human study found that intravenous VIP altered the timing of non-REM and REM sleep cycles and affected nighttime hormone secretion. It supports VIP’s involvement in sleep and circadian regulation but does not show how chronic intranasal VIP affects sleep in CIRS patients.
- Ryan JC, Shoemaker RC. RNA-Seq on patients with chronic inflammatory response syndrome treated with vasoactive intestinal peptide shows a shift in metabolic state and innate immune functions that coincide with healing. Med Res Arch. 2016;4(7). https://esmed.org/MRA/mra/article/view/862
This study used RNA sequencing to compare gene activity in CIRS patients before and after VIP treatment. The authors reported changes in metabolic and innate immune pathways that occurred alongside clinical improvement, but the study was observational and did not include a randomized control group.
- Shoemaker RC, Heyman A, Lark D. Transcriptomics and brain volumetrics define the causes of cognitive impairment in patients with CIRS and support the use of VIP in treatment. Med Res Arch. 2023;11(3). doi:10.18103/mra.v11i3.3659. https://esmed.org/MRA/mra/article/view/3659
This study examined cognitive symptoms, gene-expression patterns, and NeuroQuant brain-volume measurements in patients with CIRS. The authors reported treatment-associated changes supporting a possible role for VIP in cognitive and brain-related recovery, but the research was not a randomized trial.
- Pozo D, Anderson P, Gonzalez-Rey E. Induction of alloantigen-specific human T regulatory cells by vasoactive intestinal peptide. J Immunol. 2009;183(7):4346–4359. doi:10.4049/jimmunol.0900400. PMID:19734220. https://academic.oup.com/jimmunol/article-abstract/183/7/4346/8053336
This laboratory study found that VIP could convert activated human T cells into cells with FoxP3-positive regulatory and suppressive properties. It demonstrates meaningful immune regulation outside the body but does not establish the clinical risks or benefits of intranasal VIP.
- Gutiérrez-Cañas I, Juarranz Y, Santiago B, et al. Immunoregulatory properties of vasoactive intestinal peptide in human T cell subsets: implications for rheumatoid arthritis. Brain Behav Immun. 2008;22(3):312–317. doi:10.1016/j.bbi.2007.09.007. PMID:17951026. https://www.sciencedirect.com/science/article/abs/pii/S0889159107002486
This human immune-cell study found that VIP influenced T-cell activity in ways relevant to rheumatoid arthritis, including shifts toward regulatory, IL-10, and Th2-associated responses. It supports VIP’s immunoregulatory effects but does not establish what occurs during long-term treatment in patients.
- Yadav M, Rosenbaum J, Goetzl EJ. Cutting edge: vasoactive intestinal peptide induces differentiation of Th17 cells with a distinctive cytokine profile. J Immunol. 2008;180(5):2772–2776. doi:10.4049/jimmunol.180.5.2772. PMID:18292497. https://pubmed.ncbi.nlm.nih.gov/18292497/
In this mouse-cell laboratory study, VIP combined with TGF-β promoted the development of a distinctive type of IL-17-producing Th17 cell. The finding identifies a biologically plausible immune effect, but it does not prove that elevated blood TGF-β1 causes harmful Th17 dominance in people using intranasal VIP.
- Deng S, Xi Y, Wang H, et al. Regulatory effect of vasoactive intestinal peptide on the balance of Treg and Th17 in collagen-induced arthritis. Cell Immunol. 2010;265(2):105–110. doi:10.1016/j.cellimm.2010.07.010. PMID:20716449. https://pubmed.ncbi.nlm.nih.gov/20716449/
In a rat model of rheumatoid arthritis, VIP reduced inflammatory Th17 activity, increased regulatory T-cell activity, and improved arthritis findings. This demonstrates that VIP can have the opposite Th17 effect from reference 14 depending on the immune setting.
- Fu D, Senouthai S, Wang J, You Y. Vasoactive intestinal peptide ameliorates renal injury in a pristane-induced lupus mouse model by modulating Th17/Treg balance. BMC Nephrol. 2019;20:350. doi:10.1186/s12882-019-1548-y. PMID:31488076. https://pubmed.ncbi.nlm.nih.gov/31488076/
In a mouse model of lupus nephritis, VIP reduced Th17 cells, increased regulatory T cells, and improved proteinuria, kidney function, and autoantibody findings. This was an animal treatment model and does not establish the same effect in human autoimmune disease or CIRS.
- Jimeno R, Gomariz RP, Gutiérrez-Cañas I, et al. New insights into the role of VIP on the ratio of T-cell subsets during the development of autoimmune diabetes. Immunol Cell Biol. 2010;88(7):734–745. doi:10.1038/icb.2010.29. PMID:20309012. https://pubmed.ncbi.nlm.nih.gov/20309012/
In a mouse model of autoimmune type 1 diabetes, VIP shifted the balance away from inflammatory T-cell activity and toward regulatory immune responses, while delaying disease development. This supports context-dependent autoimmune effects but is not evidence from treated human patients.
- Li JM, Darlak KA, Southerland L, et al. VIPhyb, an antagonist of vasoactive intestinal peptide receptor, enhances cellular antiviral immunity in murine cytomegalovirus-infected mice. PLoS One. 2013;8(5):e63381. doi:10.1371/journal.pone.0063381. PMID:23723978. https://pubmed.ncbi.nlm.nih.gov/23723978/
This mouse study found that blocking VIP signaling strengthened NK-cell and CD8 T-cell antiviral responses during cytomegalovirus infection. It shows that natural VIP signaling can restrain antiviral immunity under certain experimental conditions, but it does not demonstrate that prescribed intranasal VIP causes clinically significant viral suppression.
- Kulka M, Sheen CH, Tancowny BP, Grammer LC, Schleimer RP. Neuropeptides activate human mast cell degranulation and chemokine production. Immunology. 2008;123(3):398–410. doi:10.1111/j.1365-2567.2007.02705. https://pubmed.ncbi.nlm.nih.gov/17922833/
This laboratory study found that VIP could activate cultured human mast cells, producing degranulation and the release of inflammatory cytokines and chemokines. It provides a biological reason to monitor patients with MCAS or histamine sensitivity, but it does not establish how often intranasal VIP causes MCAS flares.
- Pellesi L, Al-Karagholi MA, Chaudhry BA, et al. Two-hour infusion of vasoactive intestinal polypeptide induces delayed headache and extracranial vasodilation in healthy volunteers. Cephalalgia. 2020;40(11):1212–1223. doi:10.1177/0333102420937655. PMID:32594760. https://pubmed.ncbi.nlm.nih.gov/32594760/
In this randomized crossover study of 12 healthy volunteers, a two-hour intravenous VIP infusion caused prolonged widening of blood vessels outside the skull and delayed headache. It supports headache monitoring but does not provide a reaction rate for intermittent intranasal VIP.
- Hery M, Faudon M, Hery F. Effect of vasoactive intestinal peptide on serotonin release in the suprachiasmatic area of the rat: modulation by oestradiol. Peptides. 1984;5(2):313–317. doi:10.1016/0196-9781(84)90226-2. PMID:6473159. https://pubmed.ncbi.nlm.nih.gov/6473159/
This rat study found that VIP influenced serotonin release in the suprachiasmatic area, a brain region involved in circadian timing, and that estrogen modified the response. It shows a biological connection between VIP and serotonin signaling but does not establish a human VIP–SSRI interaction.
- Hery M, Barrit MC, Faudon M, Hery F. Effect of vasoactive intestinal peptide on serotonin metabolism in the suprachiasmatic area of the rat: mechanism of action. Peptides. 1986;7(2):183–188. doi:10.1016/0196-9781(86)90210-X. PMID:3737443. https://pubmed.ncbi.nlm.nih.gov/3737443/
This additional rat study found that VIP affected serotonin metabolism partly by inhibiting serotonin uptake in the suprachiasmatic area. The finding is relevant mechanistically, but it cannot be used to label SSRIs as a proven contraindication to intranasal VIP.
- Youssef JG, Lavin P, Schoenfeld DA, et al. The use of IV vasoactive intestinal peptide (aviptadil) in patients with critical COVID-19 respiratory failure: results of a 60-day randomized controlled trial. Crit Care Med. 2022;50(11):1545–1554. doi:10.1097/CCM.0000000000005660. PMID:36044317. https://pubmed.ncbi.nlm.nih.gov/36044317/
This randomized trial gave three days of intravenous aviptadil or placebo to 196 patients with critical COVID-19 respiratory failure. The primary recovery outcome was not statistically significant, although a secondary analysis found improved 60-day survival; the findings do not establish long-term safety or efficacy for intranasal CIRS treatment.
- U.S. Food and Drug Administration. Orphan Drug Designations and Approvals: aviptadil for sarcoidosis and pulmonary arterial hypertension. FDA orphan approval status: not FDA approved for the orphan indications. Accessed July 27, 2026. https://www.accessdata.fda.gov/scripts/opdlisting/oopd/detailedIndex.cfm?cfgridkey=751520
These FDA records show that aviptadil has received orphan-drug designations for sarcoidosis and pulmonary arterial hypertension, but it was not approved for those specific orphan indications. An orphan designation supports drug development; it is not the same as FDA approval for CIRS.
- Department of Veterans Affairs and Department of Defense. VA/DoD Clinical Practice Guideline for the Management of Major Depressive Disorder. Version 4.0. 2022. https://www.healthquality.va.gov/guidelines/MH/mdd/
This clinical guideline supports standardized assessment of depression severity and ongoing monitoring with tools such as the PHQ-9. It is not a VIP-specific guideline, but it supports using a repeatable mood baseline when psychiatric vulnerability or psychotropic medication use warrants closer monitoring.
- Weiler CR, Austen KF, Akin C, et al. AAAAI Mast Cell Disorders Committee Work Group Report: mast cell activation syndrome diagnosis and management. J Allergy Clin Immunol. 2019;144(4):883–896. doi:10.1016/j.jaci.2019.08.023. PMID:31476322. https://pubmed.ncbi.nlm.nih.gov/31476322/
This AAAAI report explains how MCAS is assessed using characteristic symptom patterns, measurable mast-cell mediators, and response to appropriate treatment. It supports structured MCAS evaluation and clinically appropriate mediator testing, but it does not provide a VIP-specific screening protocol.
- Hu WP, Li JD, Colwell CS, Zhou QY. Decreased REM sleep and altered circadian sleep regulation in mice lacking vasoactive intestinal polypeptide. Sleep. 2011;34(1):49–56. doi:10.1093/sleep/34.1.49. PMID:21203371. https://pubmed.ncbi.nlm.nih.gov/21203371/
Mice lacking VIP had less REM sleep and abnormal circadian regulation of sleep and wakefulness. This demonstrates that VIP is important to normal sleep timing, but it does not show that administered VIP causes sleep disruption or persistent fatigue in humans.
- Domschke S, Domschke W, Bloom SR, Mitznegg P, Mitchell SJ, Lux G, Strunz U. Vasoactive intestinal peptide in man: pharmacokinetics, metabolic and circulatory effects. Gut. 1978;19(11):1049–1053. doi:10.1136/gut.19.11.1049. PMID:730072. https://pubmed.ncbi.nlm.nih.gov/730072/
This is the early human study reporting an average plasma disappearance half-time of approximately one minute after intravenous infusion ended.
- Holm-Bentzen M, Christiansen J, Petersen B, Fahrenkrug J, Schultz A, Kirkegaard P. Infusion of vasoactive intestinal polypeptide in man: pharmacokinetics and effect on gastric acid secretion. Scand J Gastroenterol. 1981;16(3):429–432. doi:10.3109/00365528109181992. https://pubmed.ncbi.nlm.nih.gov/16435487/
This human study found that VIP elimination was bi-exponential, with an initial half-life of approximately two minutes and a slower phase of approximately 21 minutes.
- Burian B, Ortner A, Prassl R, Zimmer A, Mosgoeller W. Clinical potential of VIP by modified pharmaco-kinetics and delivery mechanisms. Endocr Metab Immune Disord Drug Targets. 2012;12(4):344–350. doi:10.2174/187153012803832594. PMID:23094831. https://pubmed.ncbi.nlm.nih.gov/23094831/
This review discusses VIP’s rapid enzymatic degradation, short half-life, and the importance of formulation and delivery method.
- Gonzalez-Rey E, Varela N, Chorny A, Delgado M. Therapeutical approaches of vasoactive intestinal peptide as a pleiotropic immunomodulator. Curr Pharm Des. 2007;13(11):1113–1139. doi:10.2174/138161207780618966. PMID:17430175. https://pubmed.ncbi.nlm.nih.gov/17430175/
This review supports the broader discussion of VIP’s effects on innate immunity, antigen presentation, Th1, Th2, inflammatory cytokines, and regulatory immune pathways.
- Yadav M, Goetzl EJ. Vasoactive intestinal peptide-mediated Th17 differentiation: an expanding spectrum of vasoactive intestinal peptide effects in immunity and autoimmunity. Ann N Y Acad Sci. 2008;1144:83–89. doi:10.1196/annals.1418.020. PMID:19076367. https://pubmed.ncbi.nlm.nih.gov/19076367/
This is a review of the Th17 findings and provides context for the original experimental study already listed as reference 14.
- Piggins HD, Cutler DJ. The roles of vasoactive intestinal polypeptide in the mammalian circadian clock. J Endocrinol. 2003;177(1):7–15. doi:10.1677/joe.0.1770007. PMID:12697032. https://journals.bioscientifica.com/joe/article/177/1/7/20420/The-roles-of-vasoactive-intestinal-polypeptide-in
This review supports the explanation that VIP participates in both resetting and maintaining the body’s central circadian clock.
- Jones JR, Simon T, Lones L, Herzog ED. SCN VIP neurons are essential for normal light-mediated resetting of the circadian system. J Neurosci. 2018;38(37):7986–7995. doi:10.1523/JNEUROSCI.1322-18.2018. PMID:30082421. https://www.jneurosci.org/content/38/37/7986
This mouse study supports VIP’s role in light-mediated resetting of daily rhythms. It does not establish that prescribed VIP causes persistent sleep problems in humans.
- Hamnett R, Crosby P, Chesham JE, Hastings MH. Vasoactive intestinal peptide controls the suprachiasmatic circadian clock network via ERK1/2 and DUSP4 signalling. Nat Commun. 2019;10(1):542. doi:10.1038/s41467-019-08427-3. PMID:30710088. https://www.nature.com/articles/s41467-019-08427-3
This laboratory study found rapid and sustained circadian-network responses after VIP exposure, including changes in gene activity and internal clock timing. It helps explain why downstream effects may last longer than the peptide’s plasma half-life.
- Paul S, Hanna L, Harding C, et al. Output from VIP cells of the mammalian central clock regulates daily physiological rhythms. Nat Commun. 2020;11(1):1453. doi:10.1038/s41467-020-15277-x. PMID:32193397. https://www.nature.com/articles/s41467-020-15277-x
This preclinical study found that VIP-producing clock neurons help regulate daily patterns in heart rate and corticosterone secretion
- Simon RA, Barazanji N, Jones MP, et al. Vasoactive intestinal polypeptide plasma levels associated with affective symptoms and brain structure and function in healthy females. Sci Rep. 2021;11:1406. doi:10.1038/s41598-020-80873-2. PMID:33446759. https://www.nature.com/articles/s41598-020-80873-2
This was an observational study of naturally occurring plasma VIP levels, not a trial of administered VIP. It can support the statement that VIP is related to affective and neurological pathways, but it cannot establish causation or treatment risk.
- Ago Y, Condro MC, Tan YV, et al. Reductions in synaptic proteins and selective alteration of prepulse inhibition in male C57BL/6 mice after postnatal administration of a VIP receptor (VIPR2) agonist. Psychopharmacology (Berl). 2015;232(12):2181–2189. doi:10.1007/s00213-014-3848-z. PMID:25575489. https://pubmed.ncbi.nlm.nih.gov/25575489/
This study involved repeated administration of a selective VPAC2 agonist to newborn mice during brain development. It provides mechanistic information about excessive VPAC2 signaling but should not be presented as evidence that adult intranasal VIP causes psychiatric illness.
Work With Our Trusted CIRS Functional Medicine Practitioners
Our Empower Functional Health practice is honored to be trusted CIRS functional practitioners, supporting patients and clients from around the globe. We’re passionate about helping individuals achieve root-cause healing in order to live the life they are meant to, nearly symptom-free. We provide environmental illness thought leadership and evidence-based insights, paired with clinical pearls, to help you achieve your wellness goals. We invite you to explore our free resources, and if self-troubleshooting falls short, we’re here to guide you with personalized support and protocols. If you’re interested in working one-on-one with our CIRS functional team for your environmental illness healing journey, our CIRS Discovery Call is the best place to begin.

DISCLAIMER: We share this content to help you make informed and empowered decisions about your health. However, it is provided for educational purposes only and is not intended to diagnose, treat, cure, or prevent any condition or replace individualized medical advice. Always consult with a trusted qualified healthcare practitioner before beginning a new diet, supplement, treatment, or health protocol.


